

“You can’t cross a chasm in two small jumps.” ~ David Lloyd George
Victory Friday is a weekly digest of reflections, insights, and tools from the world of functional manual and performance medicine. It is a free weekly publication. To support Victory Friday with a paid subscription, click below:
Happy Friday, all! If your low back has already been stretched, braced, medicated, and threatened with fusion, take a breath: there is a whole check-list of other body areas that need to speak up. This week: the other systems that actually keep backs from resolving, a ball TKE that stops the airport-knee buckle, a reminder that stubborn stiffness is often instability in a trench coat, and three “chronic” new clients who got fast, lasting breakthroughs once we looked past the sore spot. Blind spots first. Breakthroughs second. Dig in!
What I’m Into: Your Back Pain Isn’t Hopeless Until You’ve Done These Things. Low back pain can be highly complex and frustrating because so many factors can create and perpetuate lumbar pain and dysfunction.
For better or worse, there is so much more to back pain than:
• stretching the low back (mobility)
• doing “core stability” to the abdomen and lumbar muscles (strength)
• moving carefully (motor control; pacing)
• medications and surgery
The aforementioned quartet of strategies represents a symptoms-based approach. And while that aspect is important, full and sustained resolution — and prevention — of back pain takes a Systems (& Dimensions) Approach1.
If you or someone you know has chronic low back pain, no matter how severe and sensitive, do not:
• give in to aggressive surgery (such as lumbar fusion)
• give up on your life (work, family, recreation, hobbies)
until you have addressed and treated the following areas:
The Functional Hip. Everything below the spine heavily influences the low back. The Functional Hip — the Four-Bone System of femur, pelvis, sacrum and lumbar bones2 — must move and stabilize in a balanced, coordinated way.
The number one cause of low back pain I see in my office is a juxtaposition of this 4-bone relationship: the hip and pelvis not moving enough; the sacrum and lumbar moving too much.
A stiff hip stresses the lumbar spine. The pelvis and hip must align and move efficiently to prevent excessive strain in the low back.
The Ribcage. This is a huge one. I’ve written about the role of ribcage stiffness (namely in the diaphragm) that causes “torsions” in the pelvis: an uneven elevation and rotation of the hips, in relation to the spine.
A stiff, twisted and uneven pelvis places constant stress on the low back and, in my experience, must be mitigated for sustained resolution of low back pain and — more importantly — enhancing resilience of the low back with physical activity!
Even without overt asymmetry at the pelvis, stiffness in the diaphragm — a powerful breathing muscle with fascial connection to everywhere in the torso — can cause insidious but intractible stiffness in the low back.
Nearly all my low back clients get foam roll exercise for the ribcage, and more recently: softening strategies aimed at the diaphragm3.

The Foot and Ankle. The foot and ankle largely dictate what happens at the hip. If the foot/ankle are stiff and/or inefficient, so becomes the hip, and… see #1.
The Belly. Simply put: “The Low Back Has a Front”. And what lies in front of the lumbar spine is the belly: the organs and fascia of the viscera. The small and large intestine (as well as the uterus, for women), sit directly upon — or in close proximity to — the bones of the lumbar spine, sacrum and pelvis.
The viscera needs to be able to move…a little bit. More specifically: those bones need to move freely from the visceral structures. A “sticky belly” will adhere to and restrict or alter the motion of those bones. This subtle-but-powerful fascial force is what often creates — and stubbornly perpetuates — low back stiffness, sensitivity and pain!
Move the belly! And/or find someone to help elevate and treat the belly — especially if you or your client has a surgical, gut infection/illness, or pregnancy history!
Superficial Fascia. The outer layer of tissue — the “shrink wrap” — of the spine and pelvis is where much low back pain is sustained. Superficial fascia( just below the skin) and the thoracolumbar fascia (just deep to that) are top layers that often get “glued down” in chronic low back cases.
This fascia tension can stem from:
• trauma (impacts, like falling flat on one’s back or pelvis)
• surgery (cutting through those top layers)
• inactivity (prolonged sitting that compresses and dehydrates)
Multiple lower spinal Victories have been tied to freeing this subtle-but-stubborn layer.4 Don’t forget it!
Neck (& Head). Finally, many of the most stubborn cases of lumbar pain have contributions from the head and neck. In such cases, patients present with things like:
• pelvic elevation and mobility loss
• ribcage stiffness
• severe nerve tension in the lower body
• stubborn core strength inhibition
and no local — or even regional — treatments will resolve it.
In such cases, many have experienced a significant head and neck trauma.
Treating dysfunctional tissues in the head and neck tends to release elements down below: the diaphragm, the pelvis, and nerve tension. In such cases, the head and neck is the literal top of The Pyramid of Why5.
So if you — or a patient of yours — has intractable pain and is considering a drastic (and possibly irreversible) “next step”, be sure every one of these bases is covered!
Cool Exercises I Like. Stabilize Your Knees with Ball TKEs! I see a lot of dysfunction out in the world. And while I like to believe, “Not all imperfection is relevant”, some of it is.
Among the most problematic: knee instability due to a lack of quad control.
Interestingly, I see this most often walking in airports: people — usually older adults — walking (perhaps faster than usual, from gate to gate), but when their leg impacts the ground, the knee joint is unstable.
It may look like:
• excessive flexion (like a “blown shock” in a car)
• knee varus (outward, “bow-legged” bend)
• knee valgus
In most cases, a knee “buckle” is a quadriceps muscle stability deficit. This is the most important role of the quads in gait: to cushion the initial landing, then maintain a (mostly) straight knee as the body passes over that leg.
This stability strength deficit is most common after knee surgery, or with chronic knee pain6.
One of the best, most gait-specific ways to improve quadriceps strength to stabilize the knee is a “TKE” — a terminal knee extension exercise. This involves standing with a slightly bent knee, then slowly extending against resistance.
Most TKEs involve a resistance band, but my guy Justin Lin at Rehab & Revive recently shared this unique version of the TKE…using a resistance ball!
(Exercise begins at 3:39)
The resistance ball provides a unique challenge: both resistance in straightening (concentric work: the muscle works while shortening), and also resistance in bending, which creates an eccentric (work while lengthening) challenge. This bi-directional challenge best mimics walking, running and jumping!
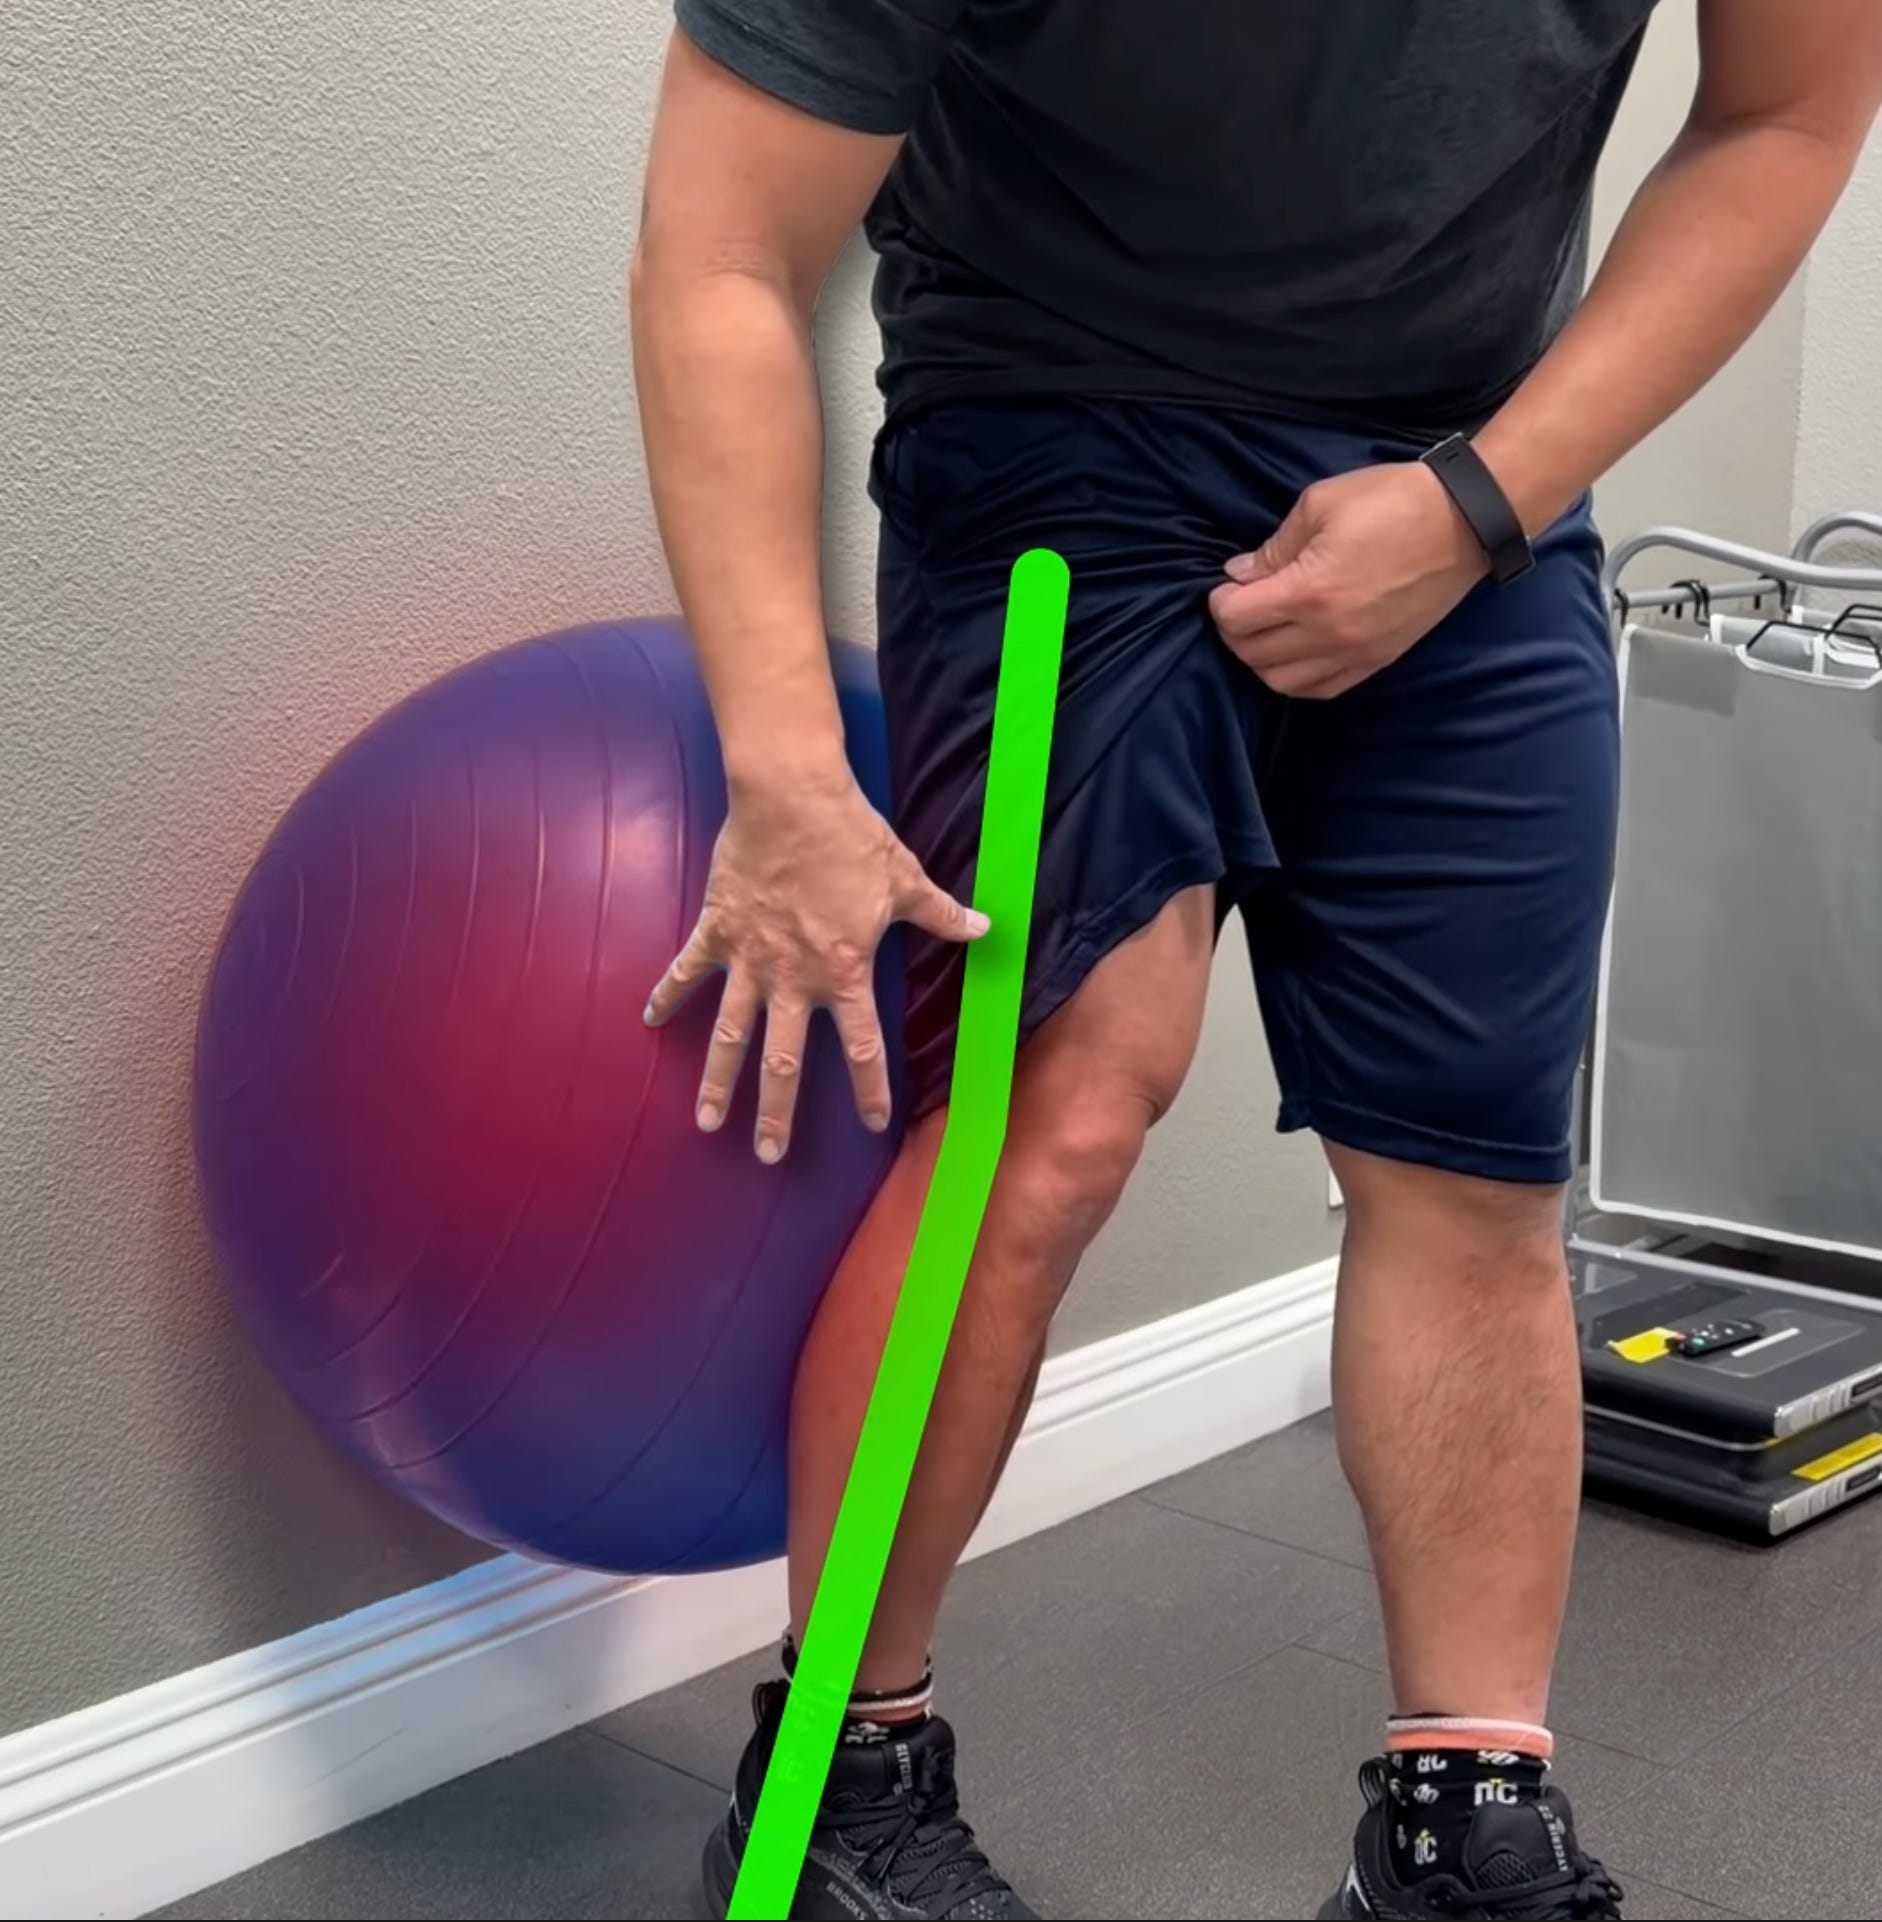
So even if you don’t have a knee injury, if you have sore or stiff knees — or you simply want to improve your stability and agility — give it a try!
Joe’s Articles. Are You Stiff or Unstable? Another Victory Friday turned publication: my post on instability-driven stiffness7.
From iRunFar.com,
Stiffness, Joint Instability, and the Strategies to Fix Them in Runners
The TL;DR:
Thesis: stubborn runner stiffness is often compensatory joint instability rather than aging, impact, or “tight tissue.”
Joint stability depends on a three-part system—passive tissues, active muscle, and neural control—and a deficit in any one can produce either extra motion or protective stiffness.
How Instability Creates Stiffness: If joints are unstable, they become uncoordinated. Stiffness develops from muscles working too hard — or getting “too beat-up” — trying to move a hypermobile system.
Problem joint areas include: the spine, shoulders, hips, and feet — while other areas may be normal or (truly) hypomobile.
Signs of instability: age-inappropriate mobility in some planes, compensatory tightness in complementary motions, “easy-come, easy-go” range after manual treatment, and rapid improvement with stability work.
Strategies to de-stiffen an unstable system: stop over-mobilizing, train joint stability with targeted exercise (lumbar core, trunk/glute control, and three-dimensional hip work), and maximize running efficiency: including neutral posture, hip hinge, and vertical hip movement strategies.
Excessive stiffness is not an inevitable byproduct of running or getting older; when stretching fails to hold, targeted stabilization is usually the more effective intervention.
Victory Friday. Beyond Blind Spots, Big Breakthroughs: Fast Wins With New (Chronic) Clients. I have had a slew of new clients recently. Most new clients that seek me out have failed other treatment approaches: other physios, medical doctors, “doctor Google/AI” (online guidance) and/or prolonged rest.
The following are a trio of new clients who had quick and sustained breakthroughs in pain, mobility, strength and function — in just one or two visits.
Why? Because we addressed a key element overlooked by those other approaches.
Most of these factors have been addressed here before at Victory Friday. These serve as reminders (for me and you) as well as fresh insight for our new readers: of key areas to address in stubborn pain:
Client: 30s yo female runner
Injury Mechanism (& When): Hamstring and hip strain with build-up toward marathon (six months ago).
Current Issue: Posterior thigh pain (both hamstring tightness and nerve symptoms), lumbopelvic pain, inability to run without pain; inability to sit for > 30 minutes without pain.
Previous (Ineffective) Approaches: Conventional physio, including both hands-on and self-mobility and strengthening to the hamstring. This resolved most of the hamstring pain.
Breakthrough Strategy: Thoracic ribcage (diaphragm) and pelvic mobilization — both areas that have suffered old impact traumas.
Result: Immediate improvement in hip and hamstring mobility; decreased pain with sitting and weightbearing
Client: 40s yo male mountainbiker
Injury Mechanism: Impact traumatic fracture of the calcaneus with internal fixation surgery (2024)
Current Issue: Chronic same-sided anterior and lateral ankle pain with impaired weightbearing, end-of-day swelling, limited work capacity, and poor impact activity tolerance.
Previous (Ineffective) Approaches: Conventional physio, including self-mobility and strengthening exercise to foot and ankle, post-operatively. Subsequent other physio and self-care strategies based on conventional foot and ankle mobility and strength.
Breakthrough Strategy: Addressing chronic tissue mobility loss from both the most recent trauma and a major trauma, 20 years ago (another impact tib-fib fracture with surgery), which caused severe superficial fascial tension and a significantly elevated fibula: mobilizing superficial fascia around the heel (surgical site), tibia and fibula (old surgery);
Result: Immediate and substantial (first-day) improvement in ankle dorsiflexion range of motion, walk gait efficiency and pain.
Client: 40s yo female runner and hiker
Injury Mechanism: Anterior hip pain during descent of a mountain (wearing heavy pack); worsened after a long trail run a few weeks later (2025)
Current Issue: Chronic hip pain and mobility loss with flexion; “zing” and “burning” pain in the anterior thigh; delayed-onset pain flares a few hours after hiking and strength work; pain with putting on shoes.
Previous (Ineffective) Approaches: Prolonged rest, self-treatment (mobility, strength) strategies.
Breakthrough Strategy: Thoracic ribcage and diaphragm mobilization to free an elevated (painful side) pelvis; visceral and neuro-fascial mobilization to the anterior thigh (including femoral nerve); femoral nerve self-stretching; 3D pelvic mobilization.
Result: Immediate and sustained improvement in hip flexion mobility (without pain), weightbearing (hiking), no “zing” pain for a week.
All three clients with “chronic pain” (stubborn pain of over six months duration; non-responsive to “conventional treatment). All three with immediate and sustained improvement in:
• pain
• mobility
• functional capacity
Most clients (and many practitioners) do not believe that such chronic, stubborn issues can improve so rapidly.
But the key for rapid improvement in chronic pain: addressing the crucial (and heretofore overlooked) system elements that are sustaining the pain and dysfunction.
Takeaways. In such new and stubborn, chronic cases I always ask two questions:
“What Hasn’t Been Done?”. Of all the things that have been tried — conventional (local and symptom-based) treatment, strength, mobility, rest — what has not been done?
These are often more System-based elements that, to many, don’t seem relevant.
For chronic hamstring pain and tightness, I hardly ever treat the hamstring the first day (or even the second): rather, I take the pressure off of it by restoring efficient alignment (not elevated and anteriorly rotated) and motion (flexion) of the pelvis8.
and,
“What’s ‘The Elephant in the Room’?” This one is a bit trickier: what’s the one thing — an objective finding, or an aspect of a patient’s medical history — that’s most significant and glaring yet — at times, for some — “hiding in plain sight?”
For my mountain biker this was both the severe lower leg fascial tension and the elevated fibula: both subtle (to the uninitiated) but quite substantial in its effect on the ankle9.
Those two questions — and an ever-developing eye for big-picture, systems-wide interactions — will get you far with even the most stubborn and severe pain.
That’s it for Issue 150!
Help people move, function and feel better: please share this publication!
Thanks for reading, and have a great weekend,

Issue 41: Systems & Dimensions. Full and sustained pain relief and recovery of function often requires a comprehensive treatment approach of multiple Systems (body areas: spine, pelvis, abdomen, pelvis, hip, knee, etc) and Dimensions (types of tissue: muscle, tendon, bone/joint, fascia, nerves, blood vessels, etc).
Issue 12: The Lower Quarter “Four-Bone System”. The functional hip is made up of four (primary) bones: femur, pelvis, sacrum, and lumbar. Each bone needs to move its share (but not too much) for efficient function without pain. A common cause of low back pain is a juxtaposition of these motions, where the hip (femur-on-pelvis) moves inadequately (or inefficiently), causing the sacrum and lumbar bones to move excessively.
Spine pain relief Victories from superficial fascial mobilization include:
Issue 77: Shrink-Wrapped Rib Release. Chronic rib stiffness and pain after trauma may be due to superficial fascial tension, adhering the ribs and paraspinals. A client with a history of repetitive falls and impacts to his ribcage developed mid-thoracic pain after a long overseas flight, and days hiking with a pack. The left mid-thorax superficial fascia was significantly adhered. Comprehensive fascial mobilization to the superficial layers, followed by paraspinals, resulted in immediate mobility restoration and pain relief with movement and breathing.
Issue 108: Fascial Freedom: Scar Mobilization Restores Lumbar Motion & Core Strength. A 60+ year old male with a history of two lumbar surgeries, but ongoing chronic lumbar pain and movement sensitivity, and abdominal core inhibition (substituting lumbar extensors) presents with severe superficial fascial tension — at his lumbar surgical scars as well as the surrounding area (thoracolumbar junction, sacrum and posterior pelvis). Comprehensive mobilization of this fascial tension resulted not only in improved mobility and decreased chronic “ache”, but it also restored normal and nearly full anterior core strength.
Issue 5: The Pyramid of Why. A root-cause treatment concept that describes how potentially multiple different — and often disparate complaints (pain, stiffness, movement issues, dysfunctions — both orthopedic and non-) are driven by a singular — and often distal and “quiet” — root cause. And only by treating “the Top of the Pyramid”, are all those issues sustainably resolved.
Paradoxically: pain inhibits muscle activation. My theory: inhibition is a “survival strategy” to prevent ongoing aggressive use of an injured joint. But after acute damage has healed, that inhibited muscle must be re-activated, otherwise it can lead to chronic instability and pain.
Issue 133: Unstable Old Guys: Signs of Instability in Older Populations. Orthopedic instability is common in older, still-active men, even when they do not appear hypermobile. It is typically isolated to one or a few joints—most often the spine, shoulder, or hip—rather than a high Beighton presentation, and it is frequently masked by chronic stiffness. Clues include age-inappropriate mobility in some planes, compensatory tightness in complementary motions, and range that returns readily with manual treatment but does not last. When stretching fails to hold, targeted stabilization exercise is often the more effective intervention.
Issue 95: You’re Stiff Because You’re Unstable. A neuromuscular stability deficit can cause real motion loss and increased “stiffness” (higher tone and resistance, and discomfort and soreness with movement). This occurs for at least two reasons: uncoordinated muscle activation causes over-activation (“tug of war”) and increased myosfacial tension; inefficient motion places tension or strain on the nervous system, which increases tone/tension to protect itself.
Issue 74: Hamstring Liberation. Chronic hamstring tension is often tied to mobility and alignment deficits in the pelvis. An anteriorly tilted—or elevated and anteriorly rotated—pelvis parks the hamstring on load, so it stays “tight,” strains, and re-tweaks after stretch-and-rest. In this athlete, a month of local hamstring care failed until the pelvis was addressed: marked SLR asymmetry (50° vs 105°+), left pelvic elevation/anterior rotation, anterior tilt, and quad–hamstring septal adhesion. Regional ribcage/diaphragm work, pelvic depression and flexion, and freeing the hamstring margins—not more hamstring massage—equalized the pelvis, normalized both SLRs, and cleared the tension.
Issue 83: Drop It Like It’s Hot: Elevating Depressed Fibulas. A high-level athlete with chronic lateral leg pain after a severe ankle sprain presented with a depressed fibula and restricted multi-planar fibular motion. Treatment combined extensive 3D myofascial release (peroneals, anterior compartment, lateral gastroc, syndesmosis), multi-directional fibular glides (bias toward superior), ankle/talar mobilization, superior-posterior compressive taping, all-day compression sleeves, and belt ankle mobilization. The result: the player returned to full competition within 24 hours and contributed to a 5-0 team record over the next six days.